
Primary Care Transformation Package Legislation Introduced in Michigan: A Meaningful Step Forward!
On August 24, 2026, Representatives Matt Longjohn (D) and Doug Wozniak (R) along with an array of cosponsors introduced an eight bill Primary Care Transformation package in the Michigan House. Michigan is in good company and now joins the ranks of over twenty other states who have looked to legislation as a lever for positive change for primary care. Here is a snapshot of the aims of the eight bills:

The proposed legislation comes at a critical juncture and lights the way for primary care to be better resourced to help to address the challenges of access and affordability. Better resourcing fuels care redesign and the opportunity to treat common issues at the primary level instead of reflexive referrals to specialists. It also provides the time with patients for ongoing guidance and care to reduce avoidable admissions and emergency department visits and manage conditions like diabetes and high blood pressure that become medical emergencies if left unmanaged. There is good evidence[1] that primary care can deliver on the promise if adequately resourced.
What would make a good primary care spending target bill even better? Provisions that would ensure that at least 80% of primary care revenue received by organizations like health systems flows down to primary care practices so that they have the resources necessary to care for their patient panels. Enforcement mechanisms would also strengthen the bill and its intent to catalyze action.
It is also important that the bill language for the investment target is specific to spending on physician-led services that form the base of primary care — family medicine, general practice, internal medicine, geriatrics, pediatrics, and geriatrics. This is important because these areas form the base of well-functioning interprofessional primary care teams and resource staff teams where primary care physicians work in partnership with nurse practitioners, medical assistants, front office staff, community health workers and other experts as appropriate for the patient panel. It is also reflective of the vision advanced in the National Academy of Science, Engineering, and Medicine’s seminal report, Implementing High-Quality Primary Care[2].
There is more to come as additional developments occur over the remainder of the year and into 2027. We are fortunate in Michigan to have such a groundswell of leaders who understand the importance of high-quality primary care to the health of Michiganders and to a well-functioning, high-value system of care.
[1] https://www.milbank.org/publications/investing-in-primary-care-the-missing-strategy-in-americas-fight-against-chronic-disease/
[2] https://www.nationalacademies.org/read/25983/chapter/3
What’s In the Proposed 2027 CMS Physician Fee Schedule for Primary Care and Population Health?
Every July, CMS releases a draft proposal describing the changes that they are proposing for the following year’s Physician Fee Schedule (PFS). After a comment period to collect public feedback, CMS finalizes the rule in November for implementation the following January. We are proud of the Michigan Multipayer Steering Committee’s comment letter submission which featured the following reflections on the proposed 2027 PFS rule and on the questions posed in their query for guidance on evolving primary care payment models:
- Using a CMMI demonstration to test waiving patient cost-sharing for Advanced Primary Care Management (APCM) Codes and Add-On Behavioral Health Integration (BHI) codes in the near term while doing the work to enable cost-sharing for all key care management codes (e.g., Chronic Care Management (CCM), Principal Care Management (PCM), Transitional Care Management (TCM), and Advanced Primary Care Management (APCM)).
- Converting G2211 to a modifier with two levels (one for clinicians in MSSP and one for those who are not) as a constructive change that rewards both complex and longitudinal care while preferentially rewarding participation in accountable care.
- Creating a new code or mechanism specific to rewarding the work associated with longitudinal primary care.
- Exempting APCM expenses from ACO benchmarking.
- Retaining the Person-Centered Primary Care Measure (PCPCM).
- Continuing the progress made to date to evolve Traditional Medicare primary care payment into a hybrid model and refine hybrid and capitated primary care approaches in managed Medicare approaches.
We are also happy to say that the Michigan Multipayer Initiatives comment letter reflects many of the themes of the comments on the 2027 proposed CMS PFS submitted by the National Academy of Science, Engineering, and Medicine’s Standing Committee on Primary Care.
Delivering Continuous, Proactive, Coordinated Care Across the Patient Panel with Advanced Primary Care
In the early 2010’s the patient-centered medical home (PCMH) model took root in primary care practices across Michigan. Over time, the model evolved to recognize the importance of team-based approaches, health-related social needs and addressing behavioral health.
Then in 2021, the National Academy of Science, Engineering, and Medicine published Implementing High-Quality Primary Care, which emphasized paying primary care practices more, and paying them differently. Better-resourced primary care practices, in turn, are better able to be proactive in partnering with patients to ensure that needed preventive services are received and that patients are better equipped and more successful in lifestyle change and chronic disease self-management. They are also able to work together to better serve patient needs in a timely and comprehensive way.
In 2025, CMS took the important step of introducing Advanced Primary Care Management (APCM) codes to fuel this delivery of comprehensive, continuous, coordinated primary care described in the 2021 NASEM report.
The APCM codes are structured to promote longitudinal, relationship-based care. What makes the APCM codes so important is that unlike so many others, they are specific to those “who are responsible for all of a patient’s primary care services and serves as the focal point for a patient’s needed health care services.” Primary care is even imbued in the name of the code set (Advanced Primary Care Management codes).
There are three CMS APCM codes (G0556, G0557, and G0558) that vary by patient complexity, from no chronic illness to two or more chronic illnesses. CMS has a helpful APCM services explainer FAQ to support practices in implementation and provision of APCM.
The CMS APCM codes bundle thirteen service elements into a single monthly payment. These service elements include: patient consent, an initiating visit, 24/7 access to care, continuity of care, comprehensive care management, care plan creation and revision, management of care transitions, coordination with community-based services, ongoing patient communication, enhanced communication using health IT, population-level data analysis, risk stratification, and performance measurement. Note that these services are not expected to be delivered each month that the code is billed; however, practices must be capable of delivering all 13 and providing them as appropriate for the patient.
The codes under the Traditional Medicare benefit structure have the customary 20% patient-cost share. Most Traditional Medicare beneficiaries have a supplemental policy that would cover the cost-share, a small portion do not. This exposes this small set of patients to financial liability for care management, severely limiting the uptake of APCM codes more broadly. Key national groups like the Primary Care Collaborative are working to free APCM codes from patient financial liability to overcome this barrier. The
2026 Evidence Report, the Primary Care Collaborative dives into the current state of APCM adoption; what factors are driving adoption; what challenges early adopters have faced; and how the primary care community perceives CMS’s latest effort to address chronic conditions. For those who are interested, on October 29th at 1:30pm ET, they will present their newest Evidence Report Release – APCM: Ensuring it Delivers Better Health.
There is national legislation that has been introduced as well to spur implementation of advanced primary care models by better resourcing primary care practices including the Patients First Act (H.R. 9693) and Pay PCPs Act of 2026 (S.B. 5269). We will continue to watch their progress in 2027.
Healthy Michigan Plan Work Requirements: Resources to Help Patients and Community Members
We’ve previously covered the upcoming introduction of work requirements for the Healthy Michigan population and now there are new resources that can be helpful for healthcare providers and community-based organization as well as for those who are helping friends and neighbors navigate coverage.
The Center for Healthcare Research and Transformation has produced an excellent piece (HR 1 and Michigan Medicaid Work Requirements) that focuses on the implementation of the requirements in Michigan including how engagement and exemption information is verified as well as lessons learned from previous efforts in other states.

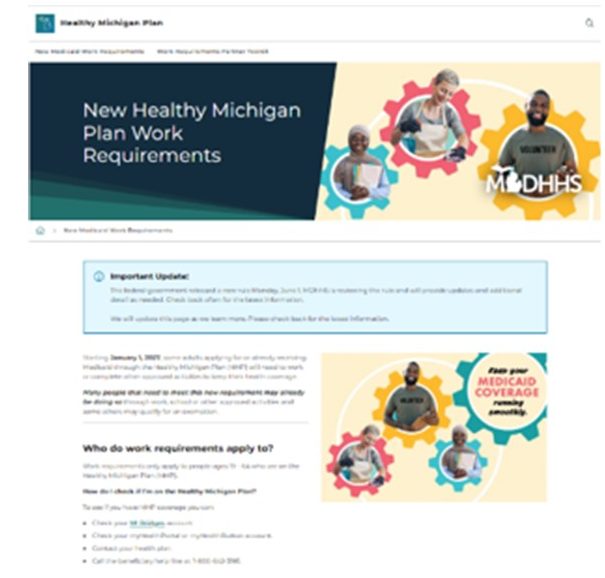
The Michigan Department of Health and Human Services (MDHHS) has also created a helpful website that provides user-friendly guidance about who the work requirements apply to as well as those who are exempt (excused) from work requirements. Specifically, they note that even if someone is on the Healthy Michigan Plan (HMP), they may be exempt (excused from meeting) work requirements if they are:
- Already subject to work requirements for food (SNAP) benefits.
- Already meeting work requirements for cash (TANF) benefits.
- Pregnant or gave birth within the past 12 months.
- A parent or caregiver of a child age 13 or under.
- A caregiver of a person(s) with a disability (someone who needs help with daily activities).
- An American Indian or Alaska Native (AI/AN).
- A person that was in foster care at age 18 and is currently younger than age 26.
- A disabled veteran.
- In a treatment program for a substance use disorder.
- In jail or prison now or in the past three months.
- A person with complex health needs, also referred to as medically frail.
- Living with a substance use disorder.
- Living with a physical, intellectual or developmental disability that makes it hard to do daily activities.
- Living with a mental health disorder.
- Living with a serious health condition that requires regular treatment.
- Experiencing temporary hardship, which is a short-term situation that may make it hard to work or complete other qualifying work activities. In these cases, you may not need to meet work requirements for a limited period of time. Temporary hardships include:
- Receiving care in a facility such as a hospital, nursing facility, psychiatric hospital, facility for people with intellectual disabilities, etc.
- Traveling outside of your community of residence for medical care for yourself or a dependent because it is not available in your community.
- Living in federally declared disaster areas.
- Living in an area with a high unemployment rate.

Also, MDHHS has created a set of resources for community-based organizations and other community partners who are working to help the people that they serve understand the changes. The Community Partner Toolkit website includes educational resources, outreach materials, and promotional tools that can be used to share information with your communities and help individuals understand these upcoming changes. Are you looking for print ads, posters, social media posts, digital graphics, and presentation decks from MDHHS about the upcoming changes? They’re all in the Community Partner Toolkit site.
2027 Comprehensive Care Conference: Save the Date
The University of Chicago’s Comprehensive Care Program is recognized nationally for its programs that effectively defragment care for complex patients. Dr. David Meltzer’s Comprehensive Care Physician (CCP) and Comprehensive Care, Community, and Culture (C4P) programs not only deliver excellent care and resources, but they are deeply interested in helping to advance the spread and uptake of these models at an even larger scale.
That is why they are holding the 2027 Comprehensive Care Conference from May 19-20 in Chicago. The conference brings together a community of practitioners with experience or interest in developing, implementing, and evaluating care models that defragment care for patients who are frequently hospitalized and often experience complex medical and social needs. Drawing on implementation science best practices, this year’s program will focus on reducing unnecessary health care utilization and costs through structuring, incentivizing, and evaluating comprehensive care model implementation.
In the meantime, their planning committee wants to hear what knowledge areas and topics you are most interested in. Please take a moment to complete this short form so we ensure the conference agenda is as valuable as possible.
Official registration and call for poster submissions will open in November, CME credit will be available, and poster sessions across both days will offer a chance to share your/your team’s work. If you know colleagues doing this work, please forward this email along!


This edition of Journal Club features a recent release by Lucy McBride, MD called Beyond the Prescription. What makes the book so interesting is its focus on helping patients become informed, prepared partners in their health care journeys. It also helps patients become more confident in chronic disease self-management, healthy behaviors, and prevention. It is written in plain-speak and available widely at local libraries as well for those who wish to give it a test run.


